Table of Contents
Thoughtful preparation can make intrauterine procedures more organized, more comfortable, and easier to follow for patients and care teams. Whether the concern involves abnormal bleeding, possible uterine polyps, fibroids, scar tissue, or a need for tissue sampling, the process should begin with a clear understanding of the clinical question and the patient’s individual needs.
Good planning does not mean that every procedure follows the same script. The appropriate setting, pain-management approach, equipment, and follow-up plan can differ substantially from one patient to another. A patient-centered plan gives people time to understand the reason for the procedure, discuss alternatives, and know what to expect before, during, and after care.
Why Planning Matters Before The Procedure
Each case benefits from a review of symptoms, imaging, relevant medical history, medications, and the suspected condition inside the uterus. This preparation helps the team anticipate whether the goal is to inspect the cavity, remove tissue, release adhesions, or obtain a biopsy. For example, a suspected polyp may call for a different setup and specimen plan than a larger fibroid or extensive scar tissue. Efficiency matters, but it should never replace safety checks, informed consent, or patient-specific clinical judgment.
What Hysteroscopy Can Help Identify And Treat
Hysteroscopy is a procedure in which a clinician uses a thin instrument with a camera to look inside the uterus. Diagnostic hysteroscopy is used to examine the uterine cavity and help clarify a concern. Operative hysteroscopy adds treatment, such as removing selected tissue or addressing adhesions, when appropriate. It may be considered for abnormal bleeding, suspected polyps, fibroids, scar tissue, or tissue sampling. Basic details of hysteroscopy include preparation, recovery, and potential risks that patients should discuss with their own clinician.
Choosing The Right Care Setting
Some hysteroscopy procedures are performed in an office, while others are completed in an outpatient surgical center or hospital. The right setting depends on the anticipated complexity, the patient’s health history, expected discomfort, anesthesia needs, available equipment, and personal preferences. Not every patient or procedure is appropriate for an office setting. Before scheduling, patients should receive clear information about pain-control options and any available alternatives.
Building A Clear Procedure Plan
- Review the clinical question. Identify what the procedure must confirm, evaluate, or treat.
- Check imaging and records. Consider the size, position, and likely type of intrauterine finding.
- Confirm informed consent. Discuss the planned procedure, reasonable alternatives, possible changes, and recovery expectations.
- Prepare the room. Verify visualization equipment, instruments, fluid supplies, specimen containers, and emergency resources.
- Assign responsibilities. Clarify who will monitor, document, handle specimens, and communicate concerns.
- Plan follow-up. Establish how pathology results, symptoms, and next steps will be reviewed.
Why Visualization And Fluid Control Matter
Clear visualization helps the clinician identify the uterine cavity, distinguish tissue of interest, and monitor progress during the procedure. Distension fluid is commonly used to gently open the cavity so it can be seen. The team should monitor fluid input and output, relevant equipment settings, and the patient’s condition throughout the case. This becomes particularly important when a procedure lasts longer or involves more extensive treatment. Reliable measurement supports timely decisions if conditions change.
How Team Communication Supports Better Workflow
A concise pre-procedure check can prevent avoidable interruptions and align the team before care begins. Useful points include patient identity, the planned treatment, anesthesia or analgesia plan, equipment readiness, fluid-monitoring responsibilities, specimen handling, and backup plans. Nurses, technicians, anesthesia professionals, and physicians each contribute important observations and actions. Documentation should capture key measurements, changes in the plan, specimens collected, and the instructions given for recovery and follow-up.
Making Patient Comfort Part Of The Plan
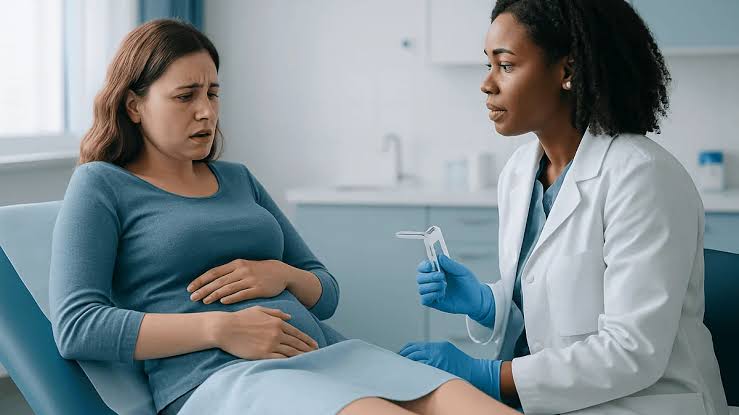
Comfort should be addressed before the day of the procedure rather than treated as an afterthought. The discussion may include medication, local anesthetic approaches, inhaled analgesia, sedation, or anesthesia, depending on the setting and clinical circumstances. Anxiety, prior medical experiences, and a patient’s preferences deserve attention. The importance of patient choice, informed consent, and appropriate pain relief is especially relevant for outpatient hysteroscopy, where a patient should be able to request a pause or stop if continuing is too painful or distressing.
Recovery, Pathology, And Follow-Up
Mild cramping or light bleeding can occur after hysteroscopy, although recovery varies with the person and the procedure performed. Patients need practical instructions about activity, medications, expected symptoms, and when to contact the care team. When tissue is removed or biopsied, a pathology review may help guide the next conversation. Heavy bleeding, fever, severe or worsening pain, fainting, or other concerning symptoms warrant prompt medical advice. Follow-up should also address whether symptoms improved and whether additional care is needed.
Questions Patients And Care Teams Should Ask
Questions For Patients
- Why is hysteroscopy recommended, and is the goal diagnosis, treatment, or both?
- Which setting is recommended for my procedure, and why?
- What pain-control options are available?
- What should I expect during recovery?
- Will tissue be sent for pathology, and when will the results be discussed?
Questions For Care Teams
- Is the planned setting appropriate for the suspected condition and the patient’s needs?
- Are the required instruments, visualization equipment, and fluid-monitoring supplies ready?
- Who will track fluid use, document measurements, and manage specimens?
- What is the escalation plan if visualization is limited or the procedure cannot be completed safely?
Final Takeaway
Better intrauterine care begins before the procedure starts. Careful preparation, clear communication, appropriate pain planning, strong visualization, fluid awareness, and dependable follow-up can support a smoother experience for patients and care teams. The best plan remains the one tailored to the patient, the clinical goal, and the judgment of the treating healthcare professionals.